

 Open access
Abstract
Background
Treatment options for malignant and aggressive glioma are limited. Vascular endothelial growth factor (VEGF) antibodies are angiogenesis inhibitors that prevent the growth of neoplasms by inhibiting the expansion of the vascular tissue that supports them. We designed this phase I trial to assess the safety and establish the maximum tolerable dose (MTD) of GB222, a recombinant human anti-VEGF monoclonal, for patients with recurrent malignant glioma.
Methods
Eligible patients were those who were diagnosed with WHO grade III and IV glioma and progressed after initial treatment including surgery, radiotherapy, and temozolomide. GB222 was initiated at 3 mg/kg (Cohort 1) intravenously once every four weeks (Q4W), then escalated in a 3 + 3 design at 5 mg/kg (Cohort 2, Q4W), 5 mg/kg (Cohort 3, Q2W), 7.5 mg/kg (Cohort 4, Q2W), and 10 mg/kg (Cohort 5, Q2W). The initial 28 days of each dose level cohort was the observation period for dose-limiting toxicity (DLT). After that, patients continued the treatment with the same dose of GB222 in combination of temozolomide if patients were considered to have benefited from the treatment. Our study also evaluated anti-tumor efficacy including objective response rate (ORR), progress free survival (PFS), and overall survival (OS), as well as pharmacokinetic parameters of GB222.
Findings
Sixteen patients were enrolled: 4 in Cohort 1, 3 each in Cohort 2, 3, 4, and 5. In the 28 days with GB222 alone, no DLT events were observed in all dose cohorts, and MTD was not reached. Among 16 patients, 14 (87.5%) received the combined treatment of GB222 and temozolomide after the DLT observation period. Two patients stopped the treatment after the DLT observation period due to disease progression. All patients (100%) reported experiencing at least one adverse event (AE) among patients who either received GB222 alone or the combination therapy of both GB222 and temozolomide. Four patients experienced grade 3/4 AE (one in Cohort 1, one in Cohort 2, and two in Cohort 3), including status epilepticus, herpes zoster, bone marrow failure, and hematological laboratory abnormalities. None of them was determined to be GB222 related. No death and treatment termination occurred due to AEs. Among these 16 patients, 81.3% (13/16) had treatment-related adverse events (TRAE). The common TRAE included decreased neutrophil count, decreased leukocyte count, increased alanine aminotransferase, hypertension, and rash. Pharmacokinetics (PK) studies showed drug exposure of GB222 had a linear relationship with the dose administrated. The overall objective response rate among 16 patients was 31.3% (95% CI: 11.02%, 58.66%) with 0% in Cohort 1, 66.7% in Cohort 2 (1 CR and 1 PR), 33.3% in Cohort 3 (1PR), 0% in Cohort 4, and 66.7% in Cohort 4 (2 PR). The median PFS was 4.44 months [95% confidence interval (CL) 2.76–6.60 months]. The median OS was 8.38 months (95% Cl: 4.24-not reached).
Interpretation
GB222 alone or combined with temozolomide had manageable safety profiles and encouraging anti-tumour activity in treating patients with recurrent HGG.
Multiprong control of glioblastoma multiforme invasiveness: blockade of pro-inflammatory signaling, anti-angiogenesis, and homeostasis restoration

Phase I trial of aflibercept (VEGF trap) with radiation therapy and concomitant and adjuvant temozolomide in patients with high-grade gliomas
Safety, tolerability, and pharmacokinetics of anti-EGFRvIII antibody–drug conjugate AMG 595 in patients with recurrent malignant glioma expressing EGFRvIII
1 Introduction
Gliomas are the most common primary brain neoplasms, accounting for 30%-40% of all intracranial tumours (Schneider, et al. 2010; Ostrom et al. 2018). In clinical practices, the diagnosis and treatment of gliomas generally follow the World Health Organization (WHO) classification and grading systems based on tumours’ histopathological and molecular features (Louis et al. 2007; Wesseling and Capper 2018). High-grade gliomas (HGG), referring to anaplastic gliomas (WHO grade III glioma) and glioblastoma multiforme (GBM, WHO grade IV glioma), are typically aggressive with poor prognosis (Park et al. 2010). The management of HGG consists of a combination of surgery, radiation therapy, and oral alkylating chemotherapy with temozolomide (Prados and Levin 2000). Studies showed that even with an optimal multimodality treatment approach (standard radiotherapy plus concomitant and adjuvant temozolomide), the 5-five survival rate of patients with GBM was less than 10% (Stupp et al. 2009; Stupp et al. 2005) and the median survival time was only 12–15 months (Quick et al. 2010). The WHO grade III tumours seemed to have a better prognosis but still not suboptimal with the median survival time being around 2–5 years (Stupp et al. 2009). By far, the treatment for HGG remains limited.
HGG has been associated with intense microvascular proliferation and angiogenesis dependent (Plate and Mennel 1995). The vascular endothelial growth factor (VEGF) is an important angiogenesis stimulator and significantly upregulated in malignant gliomas (Plate and Mennel 1995; Ferrara 2004). Therefore, targeting angiogenesis has become a therapeutic research hotspot towards malignant gliomas in recent years (Weathers and Groot 2015). VEGF(R) antibodies and other tyrosine kinase antagonists are angiogenesis inhibitors, which prevent the growth of neoplasms by inhibiting the expansion of the vascular tissue that supports them. In brain cancer, Avastin (bevacizumab) was the first approved and remains the most widely used anti-VEGF agent globally (Prager et al. 2010; AVASTIN®(bevacizumab) injection, for intravenous use Initial U.S.Approval:2004 (2020.5). 2004; ). Its use, however, is confined to second- or third-line gliomas which have failed a previous round of systemic therapy, as it has failed to demonstrate a benefit over standard chemo radiotherapy in newly diagnosed gliomas (Ameratunga, et al. 2018). Investigations of rival anti-VEGF agents for gliomas, such as the multi-targeted tyrosine kinase inhibitors lenvatinib (Hao and Wang 2020) and cabozantinib (Cloughesy et al. 2018), (Wen et al. 2018) have been suboptimal and the development of VEGF(R) antibodies remains sparse, leaving bevacizumab largely unchallenged by other drugs of its class.
GB222, developed and produced by Genor Biopharma Co., Ltd., China, is an injectable recombinant humanized anti-vascular endothelial growth factor monoclonal antibody, biosimilar with bevacizumab. GB222 and bevacizumab have the same amino acid sequence, share similar FcRn binding activities, similarity in protein structure and quality stability, comparable biological activity, pharmacodynamics, and toxicology results, and comparable preclinical pharmacokinetic results. Pharmacodynamic studies have shown that GB222 binds to human VEGF in a dose-dependent manner; to other members of the VEGF family (VEGF-B, VEGF-C, VEGF-D, PIGF, etc.) and other species (rat and mouse)) did not cross-react with VEGF; in vivo activity studies showed that both human colon adenocarcinoma cells (LS 174 T) and human rhabdoid cells (A-673) xenograft experiments in nude mice showed that GB222 could significantly inhibit tumor growth.. Pharmacokinetic studies showed that the pharmacokinetic behaviors of GB222 and bevacizumab in rhesus monkeys were basically the same at the same dose, and the two were comparable, and the relative bioavailability of GB222 was 99.01%. Therefore, it is predicted that GB222 may have the same similarity in clinical efficacy and safety. The targeted population are histologically or cytologically confirmed advanced HGG patients who have failed to respond to the standardized treatment. Here we present the primary outcomes of an open, dose-escalation, phase I clinical trial to evaluate the safety, efficacy, and pharmacokinetic characteristics of GB222 among patients with recurrent WHO III and IV gliomas.
2 Methods
This is a single-arm; open-label phase I study at three oncological medical centres in China. The study was registered in ClinicalTrials.gov (NCT04178057). The study protocol was reviewed and approved by the Institutional Review Board of the Beijing Tiantan Hospital, Capital Medical University, which is the leading clinical research centre to conduct the trial. All patients signed informed consent before being enrolled in the study. The study was conducted in accordance with the principles of the Declaration of Helsinki and Good Clinical Practice guidelines.
2.1 Eligibility criteria
Patients were eligible if they were aged ≥ 18 years with recurrent WHO grade III or IV gliomas and progressed, confirmed by magnetic resonance imaging (MRI) after initial treatment including surgery, radiotherapy, or temozolomide. Patients were required to have at least one measurable brain lesion for evaluation, with a Karnofsky performance score (KPS) ≥ 50%, an estimated survival at least three months, and with sufficient haematological, respiratory, liver, renal, and bone marrow functions. Patients were excluded if they had lesions at brainstem or meningeal spread of intracranial gliomas, or they were having a serious infection or medical illness, or serologic positivity for hepatitis A, B or C; pregnant women or those who were breastfeeding; active autoimmune diseases; severe coagulation dysfunction or obvious bleeding tendency.
2.2 GB222 dose and administration
Patients were initially given GB222 alone with dose escalation in a 3 + 3 method starting at 3 mg/kg (Cohort 1) intravenously once every four weeks (Q4W), and then escalated to 5 mg/kg Q4W (Cohort 2), 5 mg/kg Q2W (Cohort 3), 7.5 mg/kg, Q2W (Cohort 4), and 10 mg/kg Q2W (Cohort 5). The initial 28 days of each dose level cohort was the observation period for dose-limiting toxicity (DLT).
After 28 days, patients continued the treatment of the same dose of GB222 with adding in temozolomide (150 mg/day per square meters of body surface area) if patients were considered to have benefited from the treatment Approved Drug and Products: TEMODAR (Approved Drug and Products: TEMODAR (temozolomide) capsules and injection. xxxx). Body surface area was calculated using the DuBois equation of 0.20247*body weight (kg)0.425*height (m)0.725Schmidt and C., Body Surface Area (Schmidt and C., Body Surface Area (BSA).2019.p. 141–141. 2019). Treatment continued until documented disease progression, death, the occurrence of intolerable toxicity, withdrawal of informed consent by patients, loss of follow-up, or study completed.
2.3 Safety assessment
Safety assessments consisted of the monitoring and recording of adverse events (AEs) according to Common Terminology Criteria for Adverse Events version 4.0 Institute and Common terminology criteria for adverse events (Institute and Common terminology criteria for adverse events (CTCAE)Version 4.0.2009.https:, , evs.nci.nih.gov, ftp1, CTCAE, CTCAE_4.03, Archive, CTCAE_4.0_2009–05–29_QuickReference_8.5x11.pdf. 2009). DLT, defined as the occurrence of any Grade 5 AE, Grade 4 neutropenia lasting ≥ 3 days, febrile neutropenia, Grade 4 thrombocytopenia, ≥ Grade 3 non-hematologic toxicity (excluding nausea/vomiting), or > Grade 3 nausea and vomiting uncontrolled by antiemetics, was assessed during the first 28 days in a given dose cohort.
2.4 Response assessment
Patients with measurable lesions were evaluated by the contrast-enhanced brain MRI examination according to the Response Assessment in Neuro-Oncology (RANO) criteria (Sattur et al. 2016). The response of treatment was characterized into the following: objective response rate (ORR), complete response (CR), partial response (PR), stable disease (SD), progressive disease (PD). During the observation period of DLT, the efficacy of GB222 should be evaluated after each administration. The best response during DLT is the better one of the two evaluations.
2.5 Pharmacokinetic and immunogenicity studies
We also evaluate the pharmacokinetic (PK) characteristics of GB222 by collecting blood samples at pre-dose (within 30 min of drug administration), 5 min, 2-h, 8-h, 1-day, 2-day, 3-day, 5-day, 7-day, and 14-day post-dose from patients who received GB222 alone in the first treatment cycle. Serum concentrations of GB222 were determined using a validated enzyme-linked immunosorbent assay (ELISA) by United-Power Pharma Tech Co., Ltd. with a lower limit of quantification (LLOQ) of 78.13 ng/ml.
The immunogenicity of GB222 was determined by detecting anti-drug antibody (ADA) using blood samples collected at pre-dose (within 30 min of drug administration), 1-week, 2-week, 5-week, 7-week, 9-week, and 11-week post-dose. The presence of ADAs was determined by a validated immunodepletion bridging electrochemiluminescence assay with a tiered approach of screening and confirmation.
2.6 Statistical analysis
This phase I study accrued three patients per dose level and enrolled an additional three patients if one DLT was found among the first three patients in a given dose level cohort. The MTD was defined as the dose level at which no more than one over 6 patients experienced DLT. The demographic and safety data were descriptive and summarized using the percentage of occurrence in a number of patients over total patients enrolled.
Estimation of PK parameters of GB222 was performed by non-compartmental method using WinNonlin (v. 7.0; Pharsight, Mountain View, CA) software. The maximum plasma concentrations (Cmax) and time to maximum plasma concentrations (Tmax) were determined from the highest observed GB222 concentration and time of its occurrence. The area under the concentration–time curve (AUC0–24) was calculated using the linear trapezoidal method from 0–24 h. The elimination half-life (T1/2) was estimated from ln (2)/Ke, where the terminal phase elimination rate constant (Ke) was estimated using log-linear regression during the terminal phase.
The median progression-free survival (PFS) and overall survival (OS) were analysed as exploratory objectives. The definition of PFS was the time from the date of the treatment initiation to the date of documented disease progression (PD), or death, whichever occurred first. The OS was defined as the time from the treatment initiation to the date of death with any cause. The PFS and OS also used other censoring rules (such as lost-follow-up, new anti-tumour treatment initiation, withdrawing the informed consent by study participants, etc.) that were listed in the study analysis plan if the patient did not get PD or death before the data cut-off date. The median PFS and OS with 95% confidence intervals (CI) were analysed by Kaplan–Meier estimates.
3 Results
Overall, 16 patients were enrolled in the study between 25 October 2018 to 30 April 2020: 4 in Cohort 1, 3 each in Cohort 2, Cohort 3, Cohort 4, and Cohort 5. In order to observe drug-related adverse events more carefully, the first patient in cohort 1 received only one GB222 treatment during the DLT observation period, and the subsequent 3 patients received two conventional treatments. All patients progressed after the standardised therapy involved surgical resection, followed by radiotherapy with concurrent and adjuvant temozolomide. The median age of the study patients was 41 years (range: 22–62). Thirteen patients were male (81.3%). At enrolment, the two patients (12.5%) had a KPS of 90–100%, 11 (68.8%) had 70–80%, and three (18.8%) had 50–60%. Eleven patients (68.7%) were classified as WHO grade IV glioma (GBM) and five (31.3%) as WHO grade III glioma including two cases of anaplastic oligodendrogliomas and three of anaplastic astrocytoma (Table 1). All 16 patients received at least one cycle treatment, and the median follow-up was 4.02 months (range 0.92–11.2). Fourteen out of 16 (87.5%) patients received the combined treatment of GB222 and temozolomide after the DLT observation period. Two patients stopped the treatment after the DLT observation period due to disease progression.
3.1 Safety
During the DLT observation period, no DLT was identified at all dose levels. The MTD was not reached.
Adverse events were summarized in Table 2. All 16 patients (100%) reported experiencing at least one AE among patients who either received GB222 alone or the combination therapy of both GB222 and temozolomide. Four patients experienced in total 7 episodes of CTC AE v4.0 grade 3 or 4 AE (one in Cohort 1, one in Cohort 2, and two in Cohort 3). These AE included status epilepticus, herpes zoster, bone marrow failure, and hematological laboratory abnormalities. None of them was determined to be GB222 related. No treatment was terminated due to AE and no drug-related death occurred. There were two cases of severe adverse events (SAE) being observed: herpes zoster and status epilepticus, and neither of them was determined to be GB222 related (Table 2).
Thirteen out of 16 (81.3%) patients had at least one treatment-related adverse event (TRAE) with no CTC AE v4.0 G3 observed. The most common TRAE (reported in ≥ 10% of patients) included decreased neutropenia (31.3%), decreased white blood cell (25%), hypertension (18.8%), rash, headache, elevated alanine aminotransferase (ALT), elevated aspartate aminotransferase (AST), prolonged activated partial thromboplastin time (APTT), and elevated serum bilirubin (12.5% each) (Table 2).
3.2 Response assessment
All the patients received enhanced MRI at the end of each treatment cycle. Five of 16 patients had curative effects: one patient had a CR and four patients had PRs (Fig. 1) by 30 April 2020. The overall ORR was 31.3% (95% CI: 11.02%-58.66%). The highest ORR was seen in Cohort 3 and Cohort 5. No CR or PR happened in Cohort 1 and Cohort 4 (Table 3). The disease control rate (DCR) was 100% in all cohorts. The median PFS was 4.44 months [95% confidence interval (CL): 2.76–6.60 months]. All patients were alive at the 6-month after treatment. The 6-month overall survival was 100%. By 14 August 2020, 10 out of 16 patients died and 7 was diagnosed with WHO grade IV glioma at baseline. The median survival time was 8.38 months (95% Cl: 4.24-not reached).
3.3 Pharmacokinetics and immunogenicity
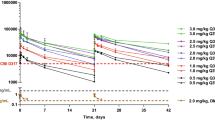
The serum concentration–time profiles of GB222 after a single intravenous infusion at the dose of 3, 5, 7.5, and 10 mg/kg are described in Fig. 2. The GB222 serum exposure increased in proportion to dose over the 3–10 mg/kg, the mean Cmax ranging from 63.85 μg/mL in Cohort 1 to 223.58 μg/mL in Cohort 5. The Tmax was 2–3 h after dosing and T1/2 was between 251.02 and 341.2 h.
Differences in GB222 exposure between antibody-positive and antibody-negative subjects were analyzed according to different immunogenicity results. In this study, 1 subject (subject number 07–003) in the 7.5 mg/kg group had a positive immunogenicity test result before administration, and a negative immunogenicity test result after administration. ADA-positive refers to baseline ADA-negative and at least one ADA-positive test after taking the drug; ADA-negative refers to baseline ADA-negative and the test results after taking the drug are all ADA-negative, that is, subjects whose baseline test results are ADA-positive are not subject to descriptive statistics. All other subjects had negative immunogenicity results. Based on the above results, no differential analysis of GB222 exposure between antibody-positive and antibody-negative subjects was performed.
4 Discussion
HGGs are difficult to treat, especially GBM which is the most aggressive form of brain cancer with a 5-year survival rate of 5–10% (Stupp et al. 2009). HGGs normally are highly vascular and rich in VEGF that promotes the process called angiogenesis (Plate and Mennel 1995). Many clinical studies have explored the treatment efficacy of anti-angiogenesis agents in the treatment of HGGs and by far, bevacizumab is the most widely used agent in this class (Ameratunga, et al. 2018). Here we demonstrated a phase I clinical trial of a biosimilar agent of bevacizumab, GB222, in treating patients with recurrent HGGs who failed the standard regimen including surgery, radiotherapy, and temozolomide.
The overall treatment was well tolerated with no DLT identification in all dosing cohorts and the MTD was not reached. The dose of GB222 with 10 mg/kg Q2W which was the same approved dose as bevacizumab (AVASTIN®(bevacizumab) injection, for intravenous use Initial U.S.Approval:2004 (2020.5). 2004) in treating patients with recurrent HGG. The safety of GB222 were similar to those previously reported with bevacizumab. In two phase II clinical trials using bevacizumab alone and in combination with irinotecan to patients with recurrent GBM (Friedman et al. 2009; Kreisl et al. 2009), the common bevacizumab associated AE were thromboembolic events and hypertensions. Similarly, we also reported hypertension in our study in three patients: two in the low dose cohort (5 mg/kg Q4W) and one in the middle dose cohort (7.5 mg/kg, Q2W). No hypertension being observed in the 10 mg/kg Q2W cohort, suggesting hypertension in GB222 might not be as frequent as in bevacizumab. Among the AEs occurred in this trial, neutropenia and leukopenia occurred more frequently in the higher GB222 dose group, but other AEs did not increase. Therefore, there may be an increase in AE due to an increase in exposure dose. More data is needed to establish this hypothesis with large patients in dose-expansion studies. We did not report thromboembolism either for arteria or vena, but we observed prolonged APTT in two patients which may indicate that GB222 might have hemorrhage risk as one of the phase II studies documented with single bevacizumab treatment to GBM (Friedman et al. 2009), therefore, more attention should be paid when designing large studies with GB222.
The antitumor response was the exploratory objective of our study. We found encouraging treatment efficacy with all patients being disease stable and 31.3% in ORR. Henry S. Friedman and his colleagues reported that bevacizumab alone and in combination with irinotecan in patients with recurrent GBM had ORR of 28.2% and 37.8%, respectively (Friedman et al. 2009). Kreisl et al. (Kreisl et al. 2009) reported that the overall radiographic response rate of treatment with the single agent of bevacizumab followed by bevacizumab plus irinotecan-based on the Levin criteria was 71% (34 PRs), whereas the response rate based on Macdonald criteria was 35% (oneCR,16PRs). The efficacy data reported in our study lied between two studies. The variations might be due to the small number of patients enrolled in our study and the different evaluation criteria used. We expected the treatment efficacy could be significant in a well-designed dose-expansion study. The median PFS of 4.44 months (95% CI: 2.76–6.60 months) and the median survival of 8.38 months observed in our study were very similar to 16 weeks in median PFS and 31 weeks in median OS reported in Kreisl’s study (Kreisl et al. 2009).
Our study was subject to some limitations. First, our study was a phase I study and by nature, it only involved a very small number of the study participants. The efficacy endpoints data could not be definitive, and we need a large dose-expansion study to confirm our findings. Second, most of our patients underwent both single agent of GB222 treatment (one cycle) and the combination therapy with both GB222 and temozolomide. However, we did not have sufficient data to compare the efficacy between the single GB222 treatment and the combined therapy. More data is needed to demonstrate the treatment efficacy of GB222 with or without temozolomide. Finally, we did not distinguish study patients as first relapse or multiple relapses after heave pre-treatments due to limited data collected, which might influence the treatment outcome differently.
5 Conclusion
In conclusion, GB222 alone or combined with temozolomide had manageable safety profiles and encouraging anti-tumour activity in treating patients with recurrent HGG.
Availability of data and materials
All data generated or analyzed during this study are included in this published article.
References
Ameratunga M, et al. Anti-angiogenic therapy for high-grade glioma. Cochrane Database Syst Rev. 2018;11(11):Cd008218.
AVASTIN® (bevacizumab) injection, for intravenous use Initial U.S. Approval: 2004 (2020.5).
Cloughesy TF, et al. Phase II study of cabozantinib in patients with progressive glioblastoma: subset analysis of patients with prior antiangiogenic therapy. Neuro Oncol. 2018;20(2):259–67.
FDA Approved Drug Products: TEMODAR (temozolomide) capsules and injection.
Ferrara N. Vascular endothelial growth factor: basic science and clinical progress. Endocr Rev. 2004;25(4):581–611.
Friedman HS, et al. Bevacizumab alone and in combination with irinotecan in recurrent glioblastoma. J Clin Oncol. 2009;27(28):4733–40.
Hao Z, Wang P. Lenvatinib in management of solid tumors. Oncologist. 2020;25(2):e302–10.
Kreisl TN, et al. Phase II trial of single-agent bevacizumab followed by bevacizumab plus irinotecan at tumor progression in recurrent glioblastoma. J Clin Oncol. 2009;27(5):740–5.
Louis DN, et al. The 2007 WHO classification of tumours of the central nervous system. Acta Neuropathol. 2007;114(2):97–109.
National Cancer Institute. Common terminology criteria for adverse events (CTCAE) Version 4.0. 2009. https://evs.nci.nih.gov/ftp1/CTCAE/ CTCAE_4.03/Archive/CTCAE_4.0_2009–05–29_QuickReference_8.5x11. pdf. .
Ostrom QT, et al. Epidemiology of intracranial gliomas. Prog Neurol Surg. 2018;30:1–11.
Park DM, Sathornsumetee S, Rich JN. Treatment and management of malignant gliomas. Nat Rev Clin Oncol. 2010;7(2):75–7.
Plate KH, Mennel HD. Vascular morphology and angiogenesis in glial tumors. Exp Toxicol Pathol. 1995;47(2–3):89–94.
Prados MD, Levin V. Biology and treatment of malignant glioma. Semin Oncol. 2000;27(3 Suppl 6):1–10.
Prager GW, et al. Targeting of VEGF-dependent transendothelial migration of cancer cells by bevacizumab. Mol Oncol. 2010;4(2):150–60.
Quick A, et al. Current therapeutic paradigms in glioblastoma. Rev Recent Clin Trials. 2010;5(1):14–27.
Sattur MG, Vogelbaum MA. Chapter 37 - RANO criteria: application to response assessment in clinical trials. In: Newton HB, editor. Handbook of neuro-oncology neuroimaging (Second Edition). San Diego: Academic Press; 2016. p. 409–18.
Schneider T, et al. Gliomas in adults. Dtsch Arztebl Int. 2010;107(45):799–807; quiz 808.
Stupp R, et al. Radiotherapy plus concomitant and adjuvant temozolomide for glioblastoma. N Engl J Med. 2005;352(10):987–96.
Stupp R, et al. Effects of radiotherapy with concomitant and adjuvant temozolomide versus radiotherapy alone on survival in glioblastoma in a randomised phase III study: 5-year analysis of the EORTC-NCIC trial. Lancet Oncol. 2009;10(5):459–66.
Weathers SP, de Groot J. VEGF manipulation in glioblastoma. Oncology (Williston Park). 2015;29(10):720–7.
Wen PY, et al. Phase II study of cabozantinib in patients with progressive glioblastoma: subset analysis of patients naive to antiangiogenic therapy. Neuro Oncol. 2018;20(2):249–58.
Wesseling P, Capper D. WHO 2016 classification of gliomas. Neuropathol Appl Neurobiol. 2018;44(2):139–50.
Witchmichen Penteado Schmidt, C. Body Surface Area (BSA). 2019. p. 141.
Acknowledgements
The authors sincerely thank all the patients for their participation in this study.
Funding
This study was fully funded by Genor Biopharma Co. Ltd., Shanghai, China.
Author information
Authors and Affiliations
Authors
Contributions
L W-B, M W-B, J C-L designed this study; KX, KZ, CF, WC performed this study; M W-B, L W–P, Q S-T, X C-Y, Y X-J, KX contributed to the patient recruitment and collected the data; KX, W L-M, GC performed the statistical analysis, and help wrote the manuscript. All authors read and approved the final manuscript.
Corresponding author
Correspondence to Wenbin Li.
Ethics declarations
Ethics approval and consent to participate
Each patients signed the consent at the time of enrolment. The trial was carried out in accordance with the Declaration of Helsinki on experimentations involving human subjects, was approved by the Institutional Ethics Review Boards of each center.
Consent for publication
Written informed consent was obtained from all patients.
Competing interests
The author Wenbin Li is a member of the Editorial Board for Current Medicine. The paper was handled by the other journal Editor and has undergone rigorous peer review process. Author Wenbin Li was not involved in the journal’s review of, or decisions related to, this manuscript. The other authors declare no competing interests.
Rights and permissions
Open Access This article is licensed under a Creative Commons Attribution 4.0 International License, which permits use, sharing, adaptation, distribution and reproduction in any medium or format, as long as you give appropriate credit to the original author(s) and the source, provide a link to the Creative Commons licence, and indicate if changes were made. The images or other third party material in this article are included in the article's Creative Commons licence, unless indicated otherwise in a credit line to the material. If material is not included in the article's Creative Commons licence and your intended use is not permitted by statutory regulation or exceeds the permitted use, you will need to obtain permission directly from the copyright holder. To view a copy of this licence, visit http://creativecommons.org/licenses/by/4.0/.
